

In most of Canada, adolescents with gender dysphoria continue to be able to access gender-affirming medical care (GAMC), the suite of hormonal interventions used to facilitate a gender transition, with few formal restrictions. Alberta has recently passed legislation limiting access to adolescents aged 16 or older, but no other province is currently seeking to regulate the provision of GAMC either through legislation or through regulatory bodies. Canadian clinicians and their organizations largely support the ability of young people with gender dysphoria, and their parents when necessary, to retain the autonomy to make decisions about accessing GAMC under their guidance, without external governmental or regulatory interference.
The use of GAMC for minors has become an exceedingly controversial and contentious subject in the public domain. Once believed to be unequivocally effective for improving the lives of gender-dysphoric children, recent studies have cast that assumption into doubt. A number of systematic reviews of the available literature have concluded that there is considerable uncertainty about whether the provision of GAMC to minors with gender dysphoria leads to more benefits than harms.
There has also been a profound rise in the number of young Canadians referred for care to Canadian gender clinics, and this rise is being driven primarily by natal females, who comprise up to 80% of young people presenting for care. Compared with earlier transition cohorts, these adolescents tend to have shorter histories of apparent gender-incongruent behaviours, higher rates of psychological comorbidity and neurodiversity, more personality disorder traits, and more frequent histories of adverse childhood experiences. The reasons behind this rise in trans identification and care-seeking for dysphoria among natal females are unknown, but it is unlikely that it is merely a matter of earlier diagnosis of a condition found at a constant level in the population over time. Rather, the speed, age distribution, and sex ratio of the increase suggest that social and cultural factors are likely shaping the emergence, recognition, expression, or persistence of gender-related distress among adolescent females.
Some proportion of this cohort will eventually receive testosterone, an intervention that can cause unmistakable and essentially irreversible changes within months, most notably voice deepening, clitoral enlargement, and facial hair development. Yet we have little population-level data showing how Canada’s liberal outlook on pediatric medical transition has shaped the uptake of GAMC, or what the implications may be. A recently published study from Oregon, a US state that has made similarly progressive policy choices around GAMC, is therefore highly instructive.
The analysis looked at data from a statewide registry of both public and private health insurance claims made on behalf of over 850,000 adolescents between 2016 and 2023 to assess the uptake of GAMC among those diagnosed with gender dysphoria. It showed that 1.5% of natal girls had received a diagnosis of gender dysphoria prior to age 18, a rate three times higher than what was seen in natal boys. And before age 18, 0,41%, or 1 out of every 241 Oregonian natal females had received testosterone.
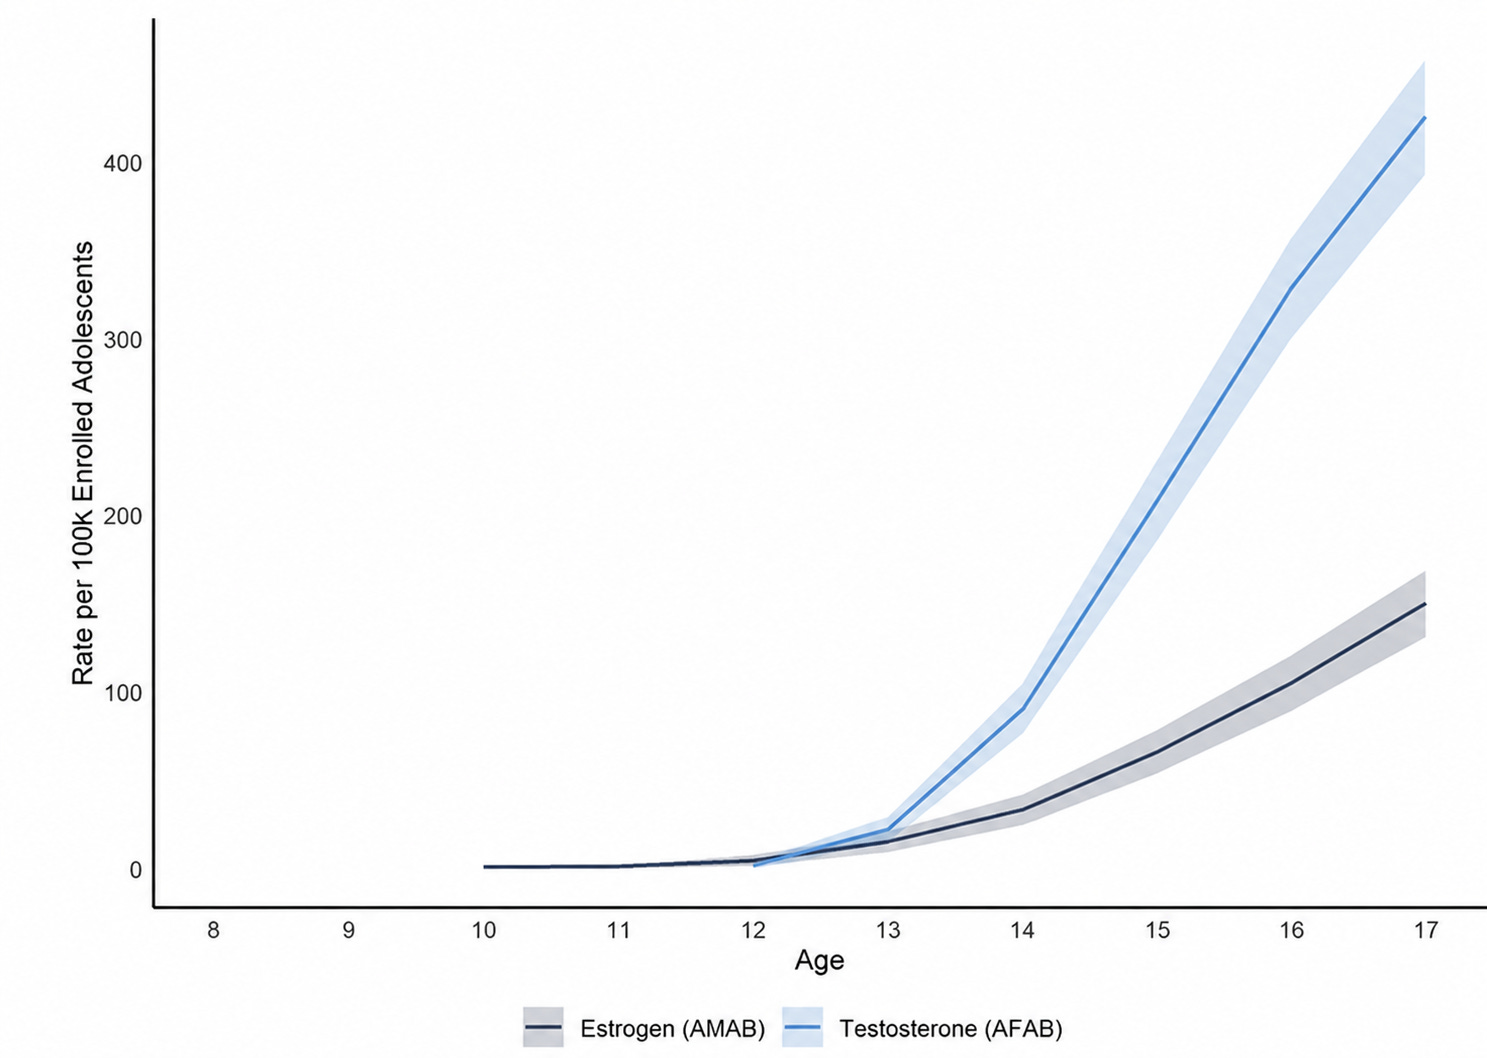
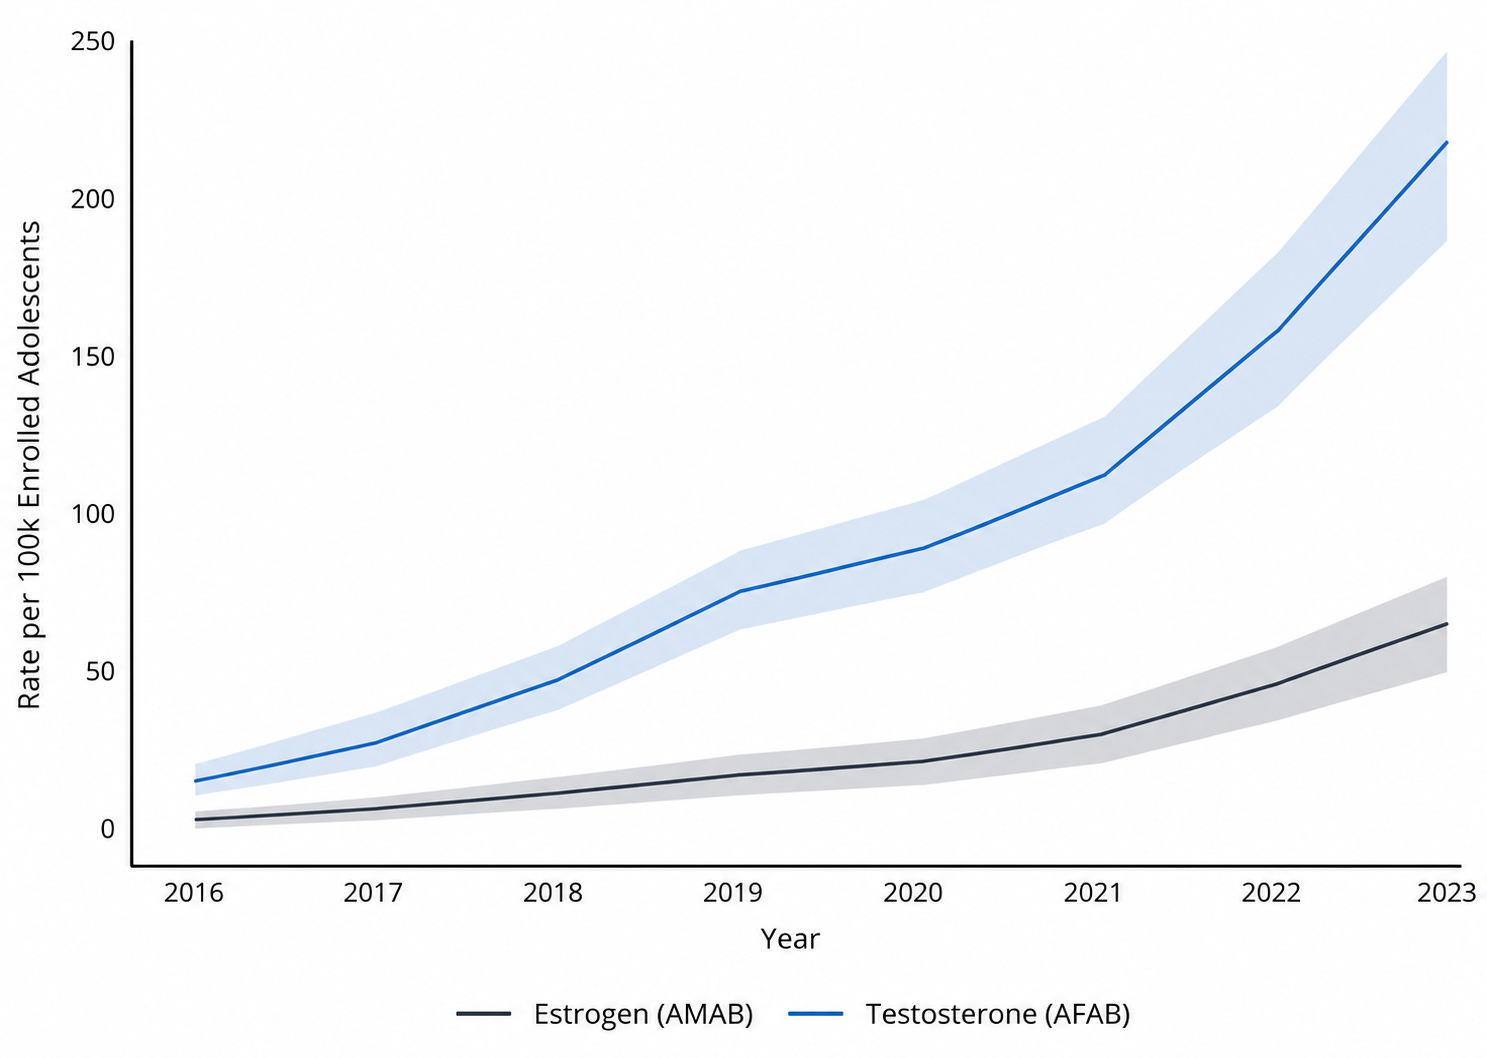
Rates of testosterone use among all natal female adolescents increased nearly ninefold over this eight-year span, from 0.028% in 2016 to 0.25% by 2023, and overall were four times higher than the rate seen in natal boys
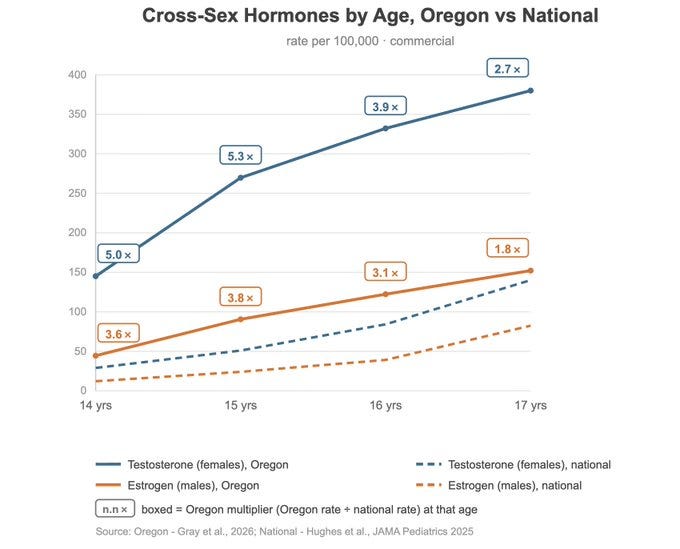
Interestingly, the prevalence of testosterone use among dysphoric natal females was 1.8 times higher than what was seen in a similarly structured analysis published one year prior, but looking at insurance data from across a more politically diverse United States. This suggests, but does not prove, that Oregon’s culture of trans acceptance and permissive policy environment may be associated with higher uptake of GAMC.
There is very little high-quality data to inform clinicians and dysphoric young people themselves about the natural trajectory of dysphoria in this modern female adolescent cohort. And while there is some evidence to suggest improvement in mental health among adult trans males who start testosterone, the evidence in adolescents is more murky. We have next to no high-quality data on how those who receive testosterone in adolescence fare over the long term in terms of mental health, and the data that do exist are often conflicting. Beyond the visible and often irreversible changes testosterone can produce, it may also have clinically relevant adverse effects on future fertility and on markers of cardiovascular and liver health. Many young people who start testosterone will also eventually pursue surgical interventions, most commonly mastectomy, which may be highly effective at reducing dysphoria but is essentially irreversible should someone later choose to detransition.
These uncertainties are compounded by the increasing visibility of natal females who, as adults, have come to regret their decision to receive GAMC as adolescents and are seeking to live again as recognizable members of their birth sex. Though evidence from adolescent gender clinics suggests that regret and pursuit of detransition prior to adulthood is rare among natal females who receive testosterone, Kinnon MacKinnon, a Canadian researcher of detransition, has argued that many detransitions occur only several years after initial transition, often beyond the time horizon captured by adolescent clinic studies. He has also suggested, as an informed estimate rather than a settled empirical finding, that 5% to 10% of this cohort may eventually detransition in adulthood.
Which raises an obvious question: given this uncertainty about the risks and benefits of long-term testosterone exposure in dysphoric natal females, how comfortable are we in Canada in continuing a set of policies and clinical norms that may be contributing to this significant rise in use? In particular, gender clinics in Canada continue publicly to support the recommendations of the 8th edition of the Standards of Care from the World Professional Association of Transgender Health, published in 2022, which extended the autonomy-centred model first articulated in the 7th edition in 2011. This model promotes the right of the adolescent, and their parents where appropriate, to make informed decisions about GAMC use. Clinicians generally perform assessments to ensure that a patient and their family are capable of providing informed consent, and to rule out major medical and psychiatric comorbidities. But in practice, many young natal females who persist in seeking testosterone will be able to receive it.
The informed consent model was implemented to grant patients and their families more autonomy over medical decision-making, and to counteract often paternalistic decision-making by clinicians that favoured young people seeking to, or claiming to, live within well-defined gender roles associated with their target sex. However, these recommendations were first made in 2011, when trans care-seeking behaviour was far less prevalent, and when stories of detransition and regret were rare. It may not be as appropriate in the current environment of rapidly rising prevalence and uncertain outcomes.
While I have intentionally limited the discussion to natal females, this does not imply that there are no concerns about GAMC in natal males. Rates of transition identification and hormone use are rising among natal males as well, though the rise is far more attenuated. There are also likely significant differences in the etiology and natural history of dysphoria between natal males and females, which may affect the likelihood of spontaneous desistance and response to GAMC. The consequentiality between estrogen and testosterone based interventions is also significant, as estrogen-induced physical changes tend to be more subtle and only breast growth, which takes place over years, would generally require surgery to reverse. It is also exceedingly rare for young trans girls to access bottom surgery as adolescents. Most natal females seek care when most visible secondary sex characteristics associated with female puberty have already developed, and thus there is usually less physical consequence to continued endogenous female hormone exposure. This is not the case for natal males, who will continue to irreversibly masculinize well into adulthood with continued natural testosterone exposure. These reasons are enough to justify why concerns about GAMC natal males and their policy implications should be considered separately.
I am not calling for an end to all access to GAMC for dysphoric natal females. I still believe that, in the right circumstances, it can and does change lives for the better. But the consequences of delaying GAMC in dysphoric females seem more manageable than they would be in males, and other less invasive interventions may exist for managing dysphoria allowing decisions around the initiation of testosterone to be deferred. Some of the most acutely distressing physiologic consequences of having a female puberty, particularly menstruation, can in many cases be substantially reduced through more reversible forms of hormonal manipulation, including continuous oral contraceptives or progestin-based methods.
Non-pharmacologic psychotherapeutic support should be routine as first-line therapy, to help young people and their families better understand the motivations and consequentiality of pursuing medical transition, and exploration of the social role should be encouraged. Even though there is scant evidence for psychological interventions being effect in facilitating spontaneous desistance or in imporving outcomes of a subsequent medical transition, there are likely minimal adverse effects related to psychotherapy. In addition, there is less of an issue in trans boys with decreasing future passability with leaving their natal puberty intact, given that most have mostly completed the development of secondary sex characteristics by the time they have presented for clinical care.
Most importantly, testosterone-based GAMC should be considered only when there is an established long-standing objective evidence of dysphoria, sustained integration in the gender role associated with the target sex, or if there is evidence of clinically meaningful worsening of mental health which can be ascribed to ongoing dysphoria despite psychological interventions.
Versions of these more measured approaches have already been adopted in other socially liberal countries in Scandinavia and Northern Europe, although it is too early to determine the impact they have had on the health of this population. But given the uncertainty around the impacts of long-term testosterone, many clinicians and policymakers would likely welcome approaches that ensure its use is more carefully targeted.
Canadian researchers are also well positioned to address some of these key data gaps. Many provinces maintain population-based registries of health care utilization and drug use, and these can be leveraged to help provide more clarity on the long-term impact of testosterone use in natal females with gender dysphoria, and the degree to which use is persistent over time. There is also the possibility of anonymously linking more granular clinic data through shared EMR platform initiatives to provide a deeper understanding of the mental wellness and social functioning of this cohort over time.
This work could be overseen by independent arm’s-length governmental authorities like the Canadian Drug Agency and the Public Health Agency of Canada, with contributions from clinicians, content experts, and patients who have engaged with adolescent gender care, ensuring that the voices of those who have had favourable and regrettable outcomes after GAMC are equally included. The goal should not be to predetermine the answer, but to generate the data Canada currently lacks, while ensuring that those who have benefited from GAMC and those who later regretted it are both treated as legitimate perspectives.
Most importantly, the sooner Canadian clinicians acknowledge and address these legitimate clinical concerns about GAMC in adolescents with gender dysphoria, the less likely it is that legislators will impose ill-considered policy changes driven more by politics than evidence. Some Canadian clinicians with direct experience in pediatric gender care have already called for a more careful review of the evidence. In light of the latest data from Oregon, it is time for others in this space to heed that call.
I would note as an aside that Scandinavia has pretty bad transition care in general, (plus scandals around breaches of medical privacy in service to anti trans researchers and really invasive sexual questioning directed at minors) so pointing to them as ‘socially liberal’ comes across as a bit of a bait and switch.
Ironically, the best way to leave detransition as a valid option is to give kids puberty blockers prior to puberty. If you want breasts later, better to have never grown them so they can be grown via hormones than to have had surgery. Which means earlier care and more aggressive use of puberty blockers.
I do appreciate you noting that care for trans girls should be examined on a separate track, since masculinization IS largely irreversible and forcing girls to grow beards and have their voices drop is a direct and long term harm, regardless of whether the care givers can pretend innocence by insisting that they did no harm; the harm was 'natural'.